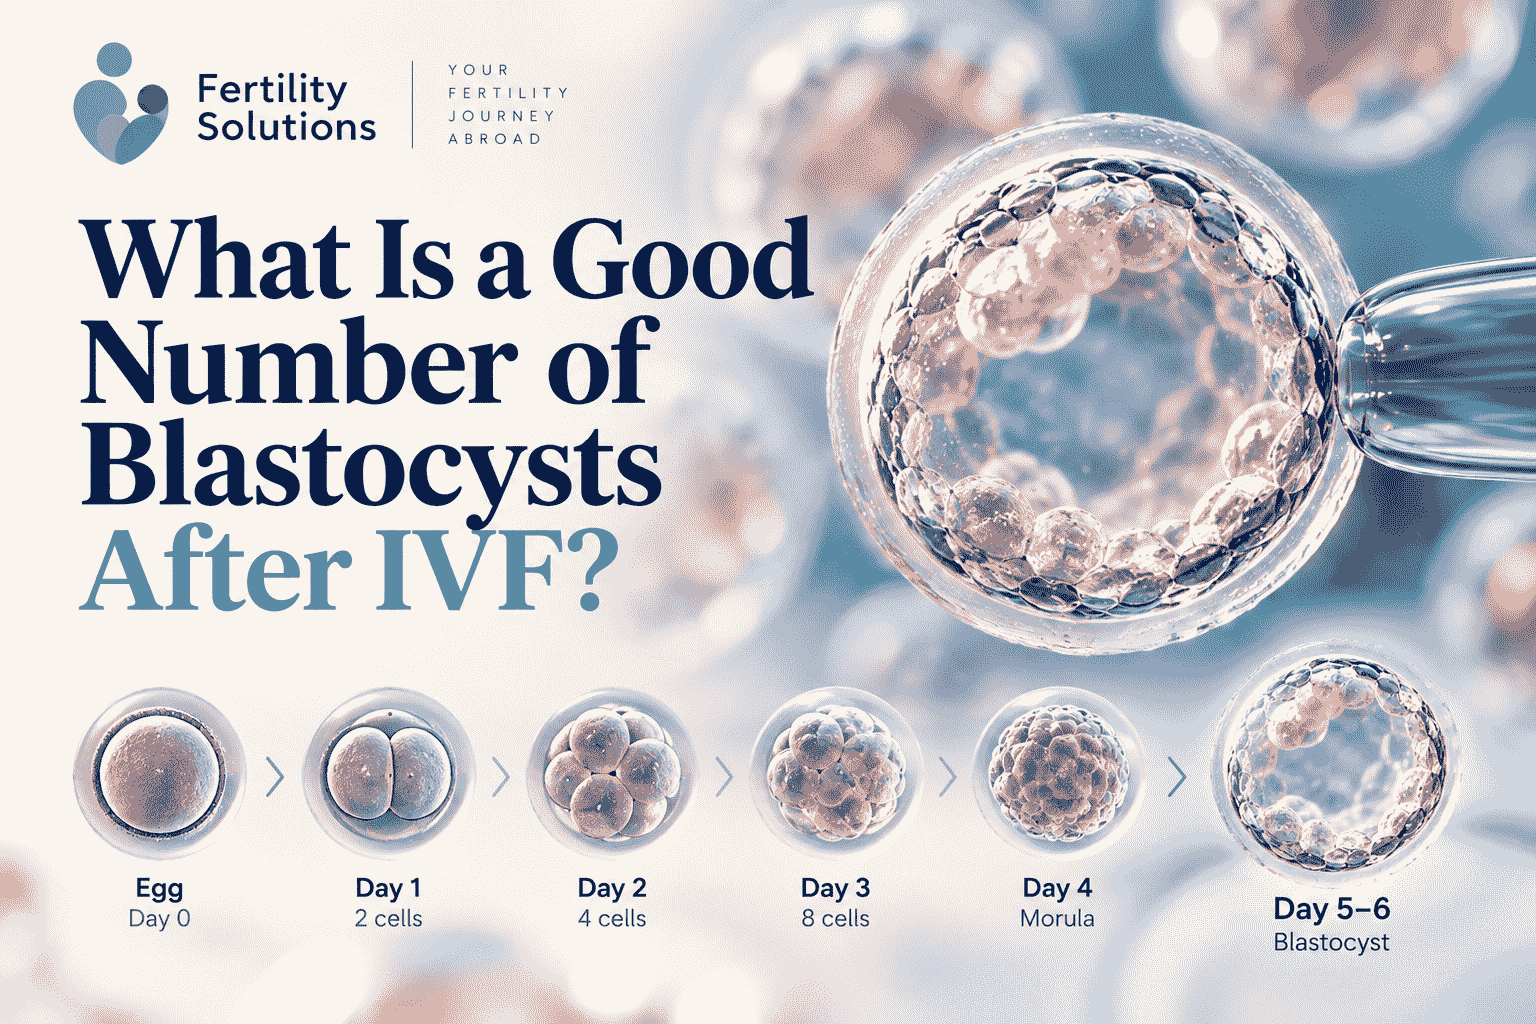
General

What Is a Good Number of Blastocysts After IVF?

What determines a good number of blastocysts after having your egg collection procedure. You may start an IVF cycle with 10 eggs, see several fertilize successfully, and then discover that only two or three embryos reached the blastocyst stage.

For many patients, this comes as a shock.

Where did all the other embryos go? Is two blastocysts enough? Should I have produced more?

One of the most important things to understand about IVF is that not every egg retrieved will become a blastocyst. There is a natural process of attrition at every stage—from egg retrieval and maturity to fertilization and embryo development.

And when it comes to blastocysts, there isn’t one number that defines a “good” IVF cycle.

Your age, egg quality, sperm quality, number of mature eggs and embryo development can all influence the final result.

Let’s look at what actually happens.

What Is a Blastocyst?

A blastocyst is an embryo that has developed for approximately five to six days after fertilization and reached an advanced stage of development.

By this point, the embryo contains many cells and begins forming two important structures:

  • The inner cell mass, which develops into the fetus
  • The trophectoderm, which contributes to the placenta

Reaching the blastocyst stage is an important developmental milestone.

This is also why many IVF clinics prefer blastocyst-stage embryo transfer or freezing when appropriate.

But not every fertilized egg will make it this far.

How Many Fertilized Eggs Normally Reach Day 5?

There is no exact percentage that applies to every IVF cycle.

It is normal for the number of embryos to decrease as development progresses.

Imagine, for example, that 10 eggs are retrieved.

Not all 10 may be mature.

Of the mature eggs, not all will fertilize.

And of those that fertilize, not all will continue developing into usable Day 5 or Day 6 blastocysts.

This gradual reduction is known as embryo attrition.

It does not necessarily mean something went wrong in the laboratory.

Embryos undergo extremely complex biological processes during their first several days of development. Some have the developmental potential to continue, while others naturally stop growing.

Age and egg quality can significantly influence this process.

How Many Embryos Should I Expect From 10 Eggs?

This is probably one of the most common questions patients ask after egg retrieval.

Unfortunately, there is no formula that can reliably tell us:

10 eggs = X blastocysts.

For example, two patients could both retrieve 10 eggs and finish their cycles with completely different results.

One patient might produce several blastocysts, while another might produce only one.

Why?

Because the number of eggs retrieved is only the beginning.

Those eggs must first be mature enough to fertilize. Fertilization must then occur successfully, and the embryos must continue developing for several days.

Factors affecting this process can include:

  • Female age
  • Egg maturity
  • Egg quality
  • Sperm quality
  • Sperm DNA integrity
  • Chromosomal abnormalities
  • Fertilization
  • Embryo development
  • Laboratory conditions
  • Individual biological variation

This is why we encourage patients not to become overly focused on the original number of eggs.

Ultimately, embryo quality and developmental potential matter more than simply having a large number of eggs retrieved.

Is One Blastocyst Enough?

Yes. One blastocyst can be enough to achieve a pregnancy.

You don’t need five or ten embryos to become pregnant.

A successful pregnancy ultimately begins with one embryo that implants and continues developing.

This is especially important for patients who feel disappointed when only one embryo reaches the blastocyst stage.

Having one blastocyst does not mean your IVF cycle has automatically failed.

However, having multiple suitable blastocysts can provide additional opportunities if the first embryo transfer is unsuccessful or if a patient hopes for more than one child.

The chance associated with an individual blastocyst depends on several factors, including:

  • Maternal age
  • Embryo quality
  • Chromosomal status, if tested
  • Uterine factors
  • Endometrial preparation
  • Transfer conditions

So rather than asking only “How many blastocysts do I have?”, it is useful to also ask:

“What do we know about the quality and developmental potential of the blastocysts I have?”

Why Do Embryos Stop Developing Before Blastocyst?

Embryo development is an extraordinarily complicated biological process.

An embryo may fertilize normally and begin dividing, only to stop developing on Day 3, Day 4 or before reaching the blastocyst stage.

This is known as embryo arrest.

There can be several possible reasons.

Chromosomal Abnormalities

Chromosomal abnormalities are an important cause of developmental arrest.

An embryo may begin dividing but contain genetic abnormalities that interfere with its ability to continue normal development.

The likelihood of chromosomal abnormalities generally increases with maternal age, although they can occur at any reproductive age.

Egg Quality

The egg provides much of the biological machinery required during the earliest stages of embryo development.

Poor egg quality can therefore contribute to abnormal fertilization or embryos stopping before the blastocyst stage.

Age is an important factor in egg quality, but it is not the only consideration.

Sperm Quality

The male partner also contributes half of the embryo’s genetic material.

Certain sperm problems, including significant DNA damage, may affect fertilization or subsequent embryo development.

This is why fertility assessment should not focus exclusively on the woman.

Natural Embryo Selection

Sometimes there is no obvious abnormality in the IVF process.

Not every fertilized egg has the biological potential to become a viable blastocyst.

Some degree of embryo attrition is expected even in apparently healthy patients.

Does Reaching Day 5 Mean an Embryo Is Chromosomally Normal?

No.

Reaching the blastocyst stage is encouraging, but it does not automatically mean that an embryo is chromosomally normal.

A blastocyst can appear morphologically excellent under the microscope and still have a chromosomal abnormality.

Likewise, embryo appearance alone cannot tell us everything about its genetic status.

When medically appropriate, PGT-A may be used to screen blastocysts for chromosome number abnormalities.

However, PGT-A is not required for every IVF patient and should be considered according to individual circumstances.

Is a Day 6 Blastocyst Still Good?

Yes.

Not every embryo develops at exactly the same speed.

Some reach the blastocyst stage on Day 5, while others require until Day 6.

Day 6 blastocysts can result in successful pregnancies and healthy births.

The day an embryo reaches blastocyst is one factor your embryology team considers, but it should not be interpreted in isolation.

Embryo morphology, developmental pattern, patient age and—where applicable—genetic testing results may also be relevant.

Is More Always Better?

Having several blastocysts can certainly be advantageous because it may provide more opportunities for embryo transfer.

But IVF is not simply a numbers competition.

Retrieving a large number of eggs does not guarantee a pregnancy, just as producing only one or two blastocysts does not mean treatment cannot succeed.

For example, one patient may produce eight blastocysts but discover through PGT-A that only a small number are euploid.

Another patient may produce only two blastocysts and achieve pregnancy from the first transfer.

This is why quantity and quality need to be considered together.

What If I Have No Blastocysts?

When none of the fertilized embryos reach blastocyst, your medical and embryology teams should review the cycle carefully.

They may consider:

  • How many eggs were retrieved
  • How many eggs were mature
  • Fertilization rate
  • The stage at which embryos stopped developing
  • Egg morphology and maturity
  • Semen analysis
  • Male-factor infertility
  • Previous IVF results
  • Ovarian stimulation response
  • Maternal age

One unsuccessful cycle does not necessarily predict exactly what will happen in another.

Your doctor may recommend modifying the stimulation protocol, investigating possible male or female factors, or discussing alternative treatment strategies depending on your individual circumstances.

Does Age Affect the Number of Blastocysts?

Age can have a significant effect on IVF outcomes because egg quality and chromosome competence change over time.

A patient may still retrieve a reasonable number of eggs at an older reproductive age, but a smaller proportion may ultimately become chromosomally normal embryos.

This is why two women who retrieve the same number of eggs can have very different IVF outcomes.

Egg number and egg quality are not the same thing.

AMH and antral follicle count can help doctors estimate ovarian reserve and expected response to stimulation, but they cannot tell us with certainty how many healthy blastocysts a patient will produce.

What Is a “Good” Number of Blastocysts?

There really isn’t one universal answer.

For one patient, five blastocysts may represent an excellent outcome.

For another patient with very low ovarian reserve, reaching the blastocyst stage with a single embryo may be a meaningful result.

Your result should be interpreted according to:

  • Your age
  • Ovarian reserve
  • Number of eggs retrieved
  • Number of mature eggs
  • Fertilization results
  • Previous IVF history
  • Sperm factors
  • Embryo development

Rather than comparing your blastocyst number with someone else’s IVF cycle, compare it with what could reasonably be expected from your individual fertility situation.

One Blastocyst Can Still Be One Opportunity

IVF involves numbers at almost every stage.

Follicles.

Eggs.

Mature eggs.

Fertilized eggs.

Day 3 embryos.

Blastocysts.

Embryo grades.

For patients, watching those numbers decrease can be emotionally difficult.

But the goal of IVF isn’t simply to finish treatment with the largest possible number of embryos.

The goal is to identify an embryo with the potential to establish a healthy ongoing pregnancy.

Sometimes there are several.

Sometimes there is only one.

And one suitable blastocyst can still represent a real opportunity for pregnancy.

If embryo development has been unexpectedly poor or repeated IVF cycles have resulted in very few or no blastocysts, the next step should be an individualized review with your fertility specialist and embryology team.

Understanding where embryo development was lost can often be more useful than simply looking at the final number.

SEO Title

What Is a Good Number of Blastocysts After IVF? Day 5 Embryos Explained

Meta Description

How many fertilized eggs normally reach Day 5? Learn how many blastocysts you might expect after IVF, whether one blastocyst can be enough, and why some embryos stop developing before blastocyst.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com

General

Meet Dr. Armağan Ulubaş – Medical Director & IVF Specialist at Clavis IVF Center

We are pleased to welcome Op. Dr. Armağan Ulubaş to Clavis IVF Center in Nicosia, North Cyprus, where he began seeing patients on September 1, 2026.

With more than 35 years of clinical experience in obstetrics, gynecology and reproductive medicine, and more than 30 years of experience in infertility care, Dr. Ulubaş brings decades of knowledge and clinical leadership to our fertility team.

He now serves as Medical Director and Physician Responsible for IVF Treatment at Clavis IVF Center, overseeing patient treatment plans and helping maintain the medical standards across our fertility programme.

With fluency in English and his native Turkish language, Dr. Ulubaş is currently welcoming both local and international patients for fertility consultations and treatment at Clavis IVF Center.

35+ Years of Experience, One Purpose

Dr. Armağan Ulubaş has dedicated his career to women’s health, obstetrics, gynecology and reproductive medicine.

After graduating from Erciyes University Faculty of Medicine in Kayseri, he completed his specialization in Obstetrics and Gynecology.

As his career developed, his attention increasingly turned toward infertility and assisted reproductive medicine. In 1998, he completed specialized training in IVF, further establishing reproductive medicine as a central focus of his medical career.

Throughout his distinguished career, Dr. Ulubaş has worked at international IVF clinics and has been involved in the diagnosis and treatment of thousands of couples from different countries.

This extensive clinical experience has given him particular insight into both straightforward and complex infertility cases, including patients who have experienced previous unsuccessful fertility treatments.

Today, he brings this experience to Clavis IVF Center in North Cyprus.

Medical Director at Clavis IVF Center

As Medical Director and IVF Specialist at Clavis IVF Center, Dr. Ulubaş plays a central role in the medical management of our fertility programme.

His responsibilities extend beyond individual consultations.

Treatment planning and important clinical decisions are carried out under his medical supervision, helping ensure that each patient receives a carefully considered and individualized approach.

His arrival at Clavis further strengthens our commitment to combining experienced fertility medicine with modern IVF laboratory technology.

Dr. Ulubaş’s Approach to Fertility Treatment

Two principles are at the heart of Dr. Ulubaş’s approach:

Scientific Honesty

Fertility treatment should begin with realistic information.

Every patient’s chances are different, and success cannot be guaranteed simply because IVF treatment has begun.

Dr. Ulubaş believes patients should receive a clear and realistic explanation of their fertility situation, available treatment options and expected chances before making important decisions.

Personalized Fertility Treatment

There is no single IVF protocol that is right for everyone.

A woman’s age, ovarian reserve, AMH level, previous IVF attempts, medical history, ultrasound findings and other fertility factors can all influence treatment.

Male fertility factors must also be carefully evaluated.

For this reason, treatment protocols at Clavis are developed according to the individual circumstances of each patient rather than applying the same approach to everyone.

IVF Treatments Available at Clavis IVF Center

With Dr. Armağan Ulubaş now welcoming patients at Clavis IVF Center, our team offers a comprehensive range of fertility treatments and assisted reproductive techniques.

Depending on the patient’s medical circumstances, treatment options may include:

  • IVF
  • ICSI
  • IUI
  • Egg donation
  • Sperm donation
  • Embryo donation
  • Egg freezing
  • Sperm freezing
  • Embryo freezing
  • Frozen embryo transfer
  • Tandem IVF cycles
  • Fertility preservation
  • Male infertility treatment
  • Surgical sperm retrieval where appropriate
  • Treatment following previous unsuccessful IVF cycles

Not every treatment or procedure is suitable for every patient. Recommendations are made after reviewing the patient’s individual fertility history and diagnostic results.

Advanced Genetic Testing and IVF

Modern fertility treatment is not limited to egg retrieval, fertilization and embryo transfer.

Genetic testing can play an important role for selected patients, particularly where there is a known inherited condition, recurrent pregnancy loss, repeated IVF failure or other relevant medical indications.

At Clavis IVF Center, patients have access to a comprehensive range of genetic testing options available in modern reproductive medicine.

Depending on the indication, this can include advanced preimplantation genetic testing and other genetic investigations.

These may include techniques such as:

PGT-A – screening embryos for chromosome number abnormalities.

PGT-M – testing embryos for specific single-gene conditions where there is a known genetic risk.

Other genetic investigations may also be considered according to the patient’s or couple’s medical and family history.

Genetic testing is not automatically necessary for every IVF patient. Dr. Ulubaş and the medical team assess whether genetic investigation is appropriate according to each individual case.

Experience Matters in Complex IVF Cases

Not every patient arrives at an IVF clinic for their first fertility treatment.

Some patients come to Clavis after several unsuccessful cycles elsewhere.

Others may have:

  • Low ovarian reserve
  • Advanced maternal age
  • Recurrent miscarriage
  • Repeated implantation failure
  • Male-factor infertility
  • Previous poor embryo development
  • Genetic concerns
  • Endometriosis
  • PCOS
  • Previous unsuccessful embryo transfers

These situations often require more than simply repeating the same IVF protocol.

They require careful examination of what happened previously and whether another approach may be appropriate.

With more than three decades of experience in infertility care, Dr. Ulubaş places particular importance on understanding a patient’s complete fertility history before determining the next step.

International Patients Are Welcome at Clavis IVF Center

Dr. Armağan Ulubaş is now accepting patients at Clavis IVF Center in Nicosia, North Cyprus.

Our clinic welcomes patients from Cyprus as well as international patients travelling for fertility treatment.

For patients coming from abroad, our international coordination team can assist throughout the process—from the first consultation and medical evaluation to treatment planning and the patient’s arrival in Cyprus.

Patients can begin by sending their previous fertility results and medical history for review before travelling.

This allows the medical team to better understand the case and begin planning the appropriate next steps.

A New Chapter for Clavis IVF Center

The appointment of Dr. Armağan Ulubaş as Medical Director marks an important new chapter for Clavis IVF Center.

His 35+ years of clinical experience, more than 30 years working with infertility patients, international IVF experience and commitment to personalized fertility medicine add another level of medical leadership to our team.

Combined with our embryology laboratory, comprehensive IVF treatments, advanced genetic testing options and multilingual international patient support, our aim is to provide each patient with treatment based on both experience and modern reproductive medicine.

Most importantly, patients should feel that their case is being looked at individually—not simply treated as another IVF cycle.

Dr. Armağan Ulubaş is now welcoming new patients at Clavis IVF Center in North Cyprus.

Whether you are considering IVF for the first time, have experienced previous unsuccessful treatments, are exploring egg donation or require advanced genetic testing, our team can review your fertility history and help determine the appropriate next steps.

SEO Title

Dr. Armağan Ulubaş | Medical Director & IVF Specialist at Clavis IVF Center

Meta Description

Meet Dr. Armağan Ulubaş, Medical Director and IVF specialist at Clavis IVF Center in North Cyprus. With 35+ years of clinical experience and more than 30 years in infertility care, he is now welcoming local and international IVF patients.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com

General

IVF Cost in Cyprus 2026: How Much Should You Expect to Pay?

When you’re considering IVF abroad, one of the first questions is usually about cost.

How much does IVF actually cost in Cyprus?

It’s a completely reasonable question. Fertility treatment is a significant financial commitment, and patients deserve to understand what they may be paying before booking flights or beginning medication. We are going to dive into IVF costs in 2026 throughout this article.

For 2026, patients working with Fertility Solutions can generally expect standard IVF/ICSI treatment to cost around €3,500, while egg donation is approximately €6,500 and embryo donation approximately €8,000.

However, IVF pricing is about more than the number at the bottom of a quote.

What is included in that price, which laboratory procedures you need, and whether additional treatment is required can all influence the final cost.

Let’s break it down.

How Much Does IVF Cost in Cyprus in 2026?

For patients planning fertility treatment in Cyprus, the approximate prices are:

Standard IVF / ICSI: Around €3,500

Standard IVF treatment using the patient’s own eggs costs approximately €3,500.

The exact amount may vary depending on your individual treatment plan and whether additional procedures are required.

Egg Donation: Around €6,500

For patients using donor eggs, treatment costs approximately €6,500.

Egg donation follows a different treatment process from conventional IVF and therefore has a different pricing structure.

Embryo Donation: Around €8,000

Embryo donation treatment is approximately €8,000.

Again, the final cost depends on the patient’s individual treatment requirements and what is included within the programme.

These figures should be considered approximate treatment prices rather than guaranteed fixed quotes.

Your individual fertility assessment allows us to provide a much clearer idea of what your complete treatment is likely to cost.

Why Is IVF More Affordable in Cyprus?

One of the main reasons international patients consider Cyprus is the opportunity to access experienced fertility care without some of the considerably higher treatment costs found elsewhere.

But affordability shouldn’t mean compromising on the areas of IVF that matter.

The experience of your doctor, embryology laboratory standards, quality control and treatment planning all play an important role.

At Fertility Solutions, our goal is to connect patients with experienced fertility clinics while keeping treatment costs accessible and clearly explained.

We work with established clinics including Crown IVF, Cyprus American IVF and Clavis IVF, helping international patients find a treatment pathway appropriate for their individual circumstances.

What Is Usually Included in an IVF Package?

This is one of the most important questions to ask when comparing IVF prices.

A clinic advertising a lower starting price may not necessarily be less expensive once additional services are added.

Depending on the treatment plan and clinic, an IVF package may include:

  • Fertility consultation
  • Treatment planning
  • Ultrasound monitoring
  • Medication protocol guidance
  • Egg retrieval
  • ICSI
  • Embryo culture and monitoring
  • Embryo transfer
  • Patient coordinator support

Certain treatments or laboratory procedures may be charged separately.

This is why we recommend looking at the complete treatment package, rather than choosing a clinic based purely on the advertised starting price.

Are IVF Medications Included?

Medication costs need to be considered separately unless your individual quote specifically states that they are included.

There isn’t one medication protocol that works for every IVF patient.

The amount and type of medication required can depend on factors such as:

  • Age
  • AMH
  • Ovarian reserve
  • Previous IVF response
  • Number of follicles
  • Individual treatment protocol

Your fertility specialist will determine your medication plan based on your individual circumstances.

Before starting treatment, make sure you understand whether medication is included in your quote or needs to be purchased separately.

Can There Be Additional IVF Costs?

Yes.

Not every patient requires additional procedures, but your doctor may recommend them depending on your fertility history.

Possible additional services can include:

  • Embryo freezing
  • Embryo storage
  • Frozen embryo transfer
  • PGT-A
  • PGT-M
  • Assisted hatching
  • Sperm freezing
  • Surgical sperm retrieval
  • Additional embryo transfers
  • Donor sperm
  • Other specialized laboratory procedures

These shouldn’t simply be added to every patient’s treatment.

Your fertility team should explain why a procedure is being recommended, what it may contribute to your treatment and what it will cost before you make a decision.

How Much Does Egg Donation Cost in Cyprus?

Egg donation treatment is approximately €6,500.

Egg donation may be considered for patients experiencing circumstances such as:

  • Significantly reduced ovarian reserve
  • Age-related decline in egg quality
  • Repeated unsuccessful IVF cycles
  • Repeated abnormal embryo development
  • Certain genetic conditions
  • Premature ovarian insufficiency

However, having low AMH or experiencing an unsuccessful IVF cycle does not automatically mean you need donor eggs.

The decision should be based on your complete fertility assessment.

For some patients who still want an opportunity to use their own eggs, other approaches—including a tandem cycle—may also be discussed before moving entirely to donor treatment.

How Much Does Embryo Donation Cost in Cyprus?

Embryo donation treatment is approximately €8,000.

Embryo donation may be considered when using either partner’s own reproductive cells is not possible or when previous fertility treatments have been unsuccessful.

Because embryo donation programmes involve different medical, laboratory and donor-related processes from conventional IVF, their cost is higher than standard IVF.

Before choosing an embryo donation programme, patients should receive clear information about the treatment process and what the quoted price includes.

What About Travel and Accommodation?

The treatment itself isn’t the only cost to consider when travelling abroad for IVF.

You’ll also need to think about:

  • Flights
  • Accommodation
  • Airport transfers
  • Local transportation
  • Medication
  • Food and everyday expenses

This is where Fertility Solutions can make the process considerably easier.

We don’t simply introduce patients to a fertility clinic and leave them to organize everything else themselves.

Our team can help coordinate the practical side of your journey, including accommodation, airport transfers, transportation and communication with your treatment team.

For international patients, having one team coordinating these details can remove a great deal of unnecessary stress.

Why Do International Patients Choose Cyprus for IVF?

Price is certainly an important reason—but it isn’t the only one.

Cyprus has become a popular destination for international fertility patients because it combines accessible treatment costs with experienced fertility professionals and modern IVF laboratories.

Its location also makes it convenient for patients travelling from:

  • The United Kingdom
  • Europe
  • The Middle East
  • Africa
  • North America

Patients also value shorter waiting times and the ability to organize much of their treatment before arriving in Cyprus.

Depending on the individual treatment plan, some preparation and medication can begin in the patient’s home country before travelling.

How Fertility Solutions Helps International IVF Patients

Travelling abroad for fertility treatment can initially seem complicated.

You may be thinking about your medical tests while simultaneously trying to organize flights, medication, accommodation and transportation.

You shouldn’t have to manage everything alone.

Fertility Solutions acts as the connection between international patients and experienced fertility clinics in Cyprus.

Our team can assist with:

  • Reviewing your initial fertility information
  • Connecting you with an appropriate IVF clinic
  • Communication with your fertility team
  • Treatment coordination
  • Pre-treatment testing
  • Medication guidance
  • Travel planning
  • Accommodation
  • Airport and ground transportation
  • Patient support throughout treatment

Our aim is to make the process feel organized from your first conversation through your treatment in Cyprus.

Is the Cheapest IVF Clinic Always the Best Choice?

Not necessarily.

Price matters, particularly when fertility treatment already represents a major financial commitment.

But IVF isn’t something that should be chosen based on price alone.

When comparing clinics, consider:

  • The experience of the fertility doctor
  • The experience of the embryology team
  • Laboratory standards
  • Available IVF technology
  • How your treatment is personalized
  • Communication and patient support
  • What the quoted price actually includes

Remember that your embryos spend some of their most important first days inside an embryology laboratory.

Laboratory quality therefore matters just as much as the consultation room.

The aim should be to find good value without sacrificing medical and laboratory quality.

How Do I Get an Exact IVF Price?

Online prices are useful for understanding what to expect, but your exact treatment cost can only be determined after your individual circumstances are reviewed.

Your fertility team may need information including:

  • Your age
  • AMH result
  • Ultrasound findings
  • Previous IVF history
  • Previous pregnancies or miscarriages
  • Semen analysis
  • Relevant medical history
  • Previous fertility tests
  • Whether donor treatment is being considered

Once this information has been reviewed, a personalized treatment plan can be prepared.

This allows you to understand not only the expected cost, but also why each part of your treatment has been recommended.

IVF Cost in Cyprus 2026: At a Glance

For patients considering fertility treatment in Cyprus in 2026, approximate prices are:

IVF / ICSI — around €3,500

Egg Donation — around €6,500

Embryo Donation — around €8,000

Additional procedures, medications, travel and accommodation may affect the overall cost depending on your individual treatment plan.

Final Thoughts

Cyprus continues to offer international patients an opportunity to access fertility treatment at comparatively affordable prices.

But when you’re comparing IVF costs, don’t stop at the number advertised on a website.

Ask what is included.

Ask whether medication is separate.

Ask whether additional laboratory procedures may be recommended.

And most importantly, ask who will be responsible for your treatment and your embryos.

At Fertility Solutions, we help patients understand both the medical and practical sides of travelling to Cyprus for fertility treatment.

From connecting you with an experienced fertility clinic to coordinating your treatment, accommodation and transportation, our goal is to make the journey as straightforward and transparent as possible.

For 2026, you can expect IVF/ICSI treatment to cost approximately €3,500, egg donation approximately €6,500, and embryo donation approximately €8,000.

We understand that IVF costs play a big role determining decision making when it comes to choosing a clinic, but the experience of that clinic, as well as the success rates play crucial roles. Your fertility journey is personal.

Your treatment plan—and your quote—should be too.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com
General

What Is a Mosaic Embryo? What PGT-A Results Really Mean

Receiving your PGT-A results can sometimes create more questions than answers.

You may expect embryos to be classified simply as “normal” or “abnormal,” only to discover that one of your embryos has been reported as mosaic.

So, what exactly does that mean?

A mosaic result generally means that the cells sampled during PGT-A showed a mixture of apparently chromosomally normal and abnormal cells.

Importantly, a mosaic embryo isn’t necessarily the same as an aneuploid embryo. Some mosaic embryos have resulted in healthy pregnancies and healthy babies, which is why their potential use has become an important—and sometimes complicated—conversation in modern IVF.

Let’s break down what patients should know.

What Is a Mosaic Embryo?

Normally, human cells contain 46 chromosomes arranged in 23 pairs.

During embryo development, cells divide rapidly. Sometimes an error occurs during this process and different cells can end up with different chromosome findings.

When PGT-A analyzes a small sample of cells from a blastocyst, the laboratory may detect a mixture of apparently normal and abnormal chromosome signals.

This may be reported as mosaicism.

A PGT-A result is based on cells biopsied from the trophectoderm, which develops primarily into the placenta. It does not test every cell of the embryo.

This is one reason mosaic PGT-A results require careful interpretation.

Can Mosaic Embryos Become Healthy Babies?

Yes, they can.

Healthy pregnancies and births have been reported following the transfer of embryos classified as mosaic by PGT-A.

However, that does not mean every mosaic embryo has the same reproductive potential.

The outcome may depend on factors such as:

  • Which chromosome is involved
  • Whether the finding involves a whole chromosome or part of one
  • The reported level of mosaicism
  • Embryo quality
  • The specific PGT-A laboratory and testing platform

In general, mosaic embryos may have lower implantation rates and higher miscarriage rates than euploid embryos, although outcomes vary considerably depending on the particular finding.

This is why mosaic embryo transfer should be considered individually rather than treating every mosaic embryo as belonging to one category.

What Is the Difference Between Mosaic and Aneuploid Embryos?

Understanding the terminology makes PGT-A reports much easier to interpret.

Euploid Embryo

A euploid result means the tested sample showed the expected chromosome number.

When available, euploid embryos are generally prioritized for transfer.

Mosaic Embryo

A mosaic result indicates a mixture of normal and abnormal chromosome signals within the biopsy sample.

Some mosaic embryos may retain reproductive potential.

Aneuploid Embryo

An aneuploid result indicates that the tested cells showed an abnormal number of chromosomes, such as an extra or missing chromosome.

These embryos generally have a much lower chance of producing a healthy ongoing pregnancy, although PGT-A remains a screening test rather than a diagnosis of every cell in an embryo.

So, in simplified terms:

Euploid → expected chromosome result

Mosaic → mixture of signals

Aneuploid → abnormal chromosome result

The reality is more complicated than these three labels, which is why PGT-A reports should be interpreted with your fertility specialist and, where appropriate, a genetic counselor.

Should Mosaic Embryos Be Transferred?

Sometimes—but not automatically.

If a patient has both euploid and mosaic embryos available, a euploid embryo would generally be prioritized.

The question becomes more difficult when no euploid embryos remain.

For example, imagine a patient completes IVF and receives the following PGT-A results:

  • No euploid embryos
  • One or more aneuploid embryos
  • One mosaic embryo

In this situation, the mosaic embryo may deserve further evaluation rather than being automatically discarded.

Your fertility specialist and genetic counselor can review the specific result and discuss the potential benefits, limitations and risks of transfer.

Factors considered may include:

  • Type of mosaicism
  • Chromosome involved
  • Level of mosaicism reported
  • Patient age
  • Previous IVF history
  • Availability of other embryos
  • Possibility of another egg retrieval

The decision should always be personalized.

Does Mosaicism Affect Miscarriage Risk?

It can.

Compared with euploid embryo transfers, mosaic embryo transfers as a group have been associated with a higher risk of implantation failure and miscarriage.

But the risk is not identical for every mosaic embryo.

Some mosaic embryos implant and develop normally, while others fail to implant or miscarry.

This is another reason why the exact PGT-A finding matters.

A laboratory report that simply says “mosaic” doesn’t tell the entire story.

Patients should discuss the specific chromosome finding and reported mosaic level with professionals experienced in interpreting PGT-A results.

If a Mosaic Embryo Implants, Will the Baby Have a Chromosomal Condition?

Not necessarily.

Healthy babies have been born following mosaic embryo transfers.

However, because PGT-A is a screening test and a mosaic result creates additional uncertainty, genetic counseling is especially important.

If pregnancy occurs following mosaic embryo transfer, your healthcare team may discuss prenatal diagnostic testing such as chorionic villus sampling (CVS) or amniocentesis, depending on the particular circumstances.

Standard prenatal screening tests and diagnostic tests are not the same, so your obstetric and genetics teams can explain which approach is appropriate.

Why Can PGT-A Detect Mosaicism?

PGT-A examines a small number of cells removed from the outer portion of a blastocyst.

Modern genetic testing is sensitive enough to detect chromosome signals that appear to contain a mixture of normal and abnormal cells.

However, interpreting those signals is complicated.

The biopsy represents only a small sample of the embryo, and laboratories can use different thresholds and reporting practices when classifying mosaic results.

Therefore, PGT-A shouldn’t be thought of as a perfect photograph of every cell inside an embryo.

It is a sophisticated screening tool that provides information doctors can use alongside the patient’s broader clinical picture.

Can a Mosaic Embryo Be Your Only Embryo?

Yes.

This can be one of the most difficult situations for IVF patients.

After stimulation, egg retrieval, fertilization, blastocyst development and PGT-A, a mosaic embryo may sometimes be the only embryo remaining with potential for consideration.

At this point, there isn’t one answer that is right for everyone.

Some patients may decide to attempt another egg retrieval in the hope of creating a euploid embryo.

Others—particularly when another retrieval is unlikely or difficult—may want to discuss whether their mosaic embryo could reasonably be considered for transfer.

Neither decision should be made from the word “mosaic” alone.

The complete genetic report matters.

Should I Do Another Egg Retrieval Instead?

That depends on your circumstances.

Another retrieval may be considered when:

  • The patient is younger
  • Ovarian reserve remains reasonable
  • Another cycle is medically appropriate
  • There is a realistic opportunity to create additional embryos

For patients with advanced maternal age, very low ovarian reserve or several unsuccessful cycles, the discussion may be different.

Options might eventually include another retrieval, transfer of an appropriately evaluated mosaic embryo, a tandem cycle or egg donation.

The goal isn’t to follow the same rule for every patient.

It’s to understand the realistic options and choose the approach that makes sense for that individual.

Final Thoughts

A mosaic PGT-A result can initially sound frightening, but mosaic does not automatically mean an embryo has no potential.

Healthy pregnancies and births have occurred after mosaic embryo transfer.

At the same time, mosaic embryos shouldn’t be treated exactly like euploid embryos. Implantation rates may be lower, miscarriage risk may be higher, and the specific chromosome finding can significantly influence the conversation.

If you receive a mosaic result, don’t make a decision based solely on a label.

Ask your fertility specialist:

Which chromosome is involved? How was the mosaicism classified? What does the laboratory report actually show? And what alternatives do I have?

When mosaic embryo transfer is being considered, genetic counseling can be an especially valuable part of that decision.

PGT-A gives us important information—but understanding what that information means for your particular embryo and your particular fertility journey is what matters most.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com
General

What Happens If PGT-A Shows No Normal Embryos? Understanding Your Next Options

There is a chance that PGT-A can show no normal embryos. Going through IVF and reaching the blastocyst stage can already feel like a major achievement. So when PGT-A results come back showing no chromosomally normal—or euploid—embryos, it can be incredibly disappointing.

For many patients, the immediate question is:

“Does this mean I can’t have a healthy baby with my own eggs?”

Not necessarily.

One IVF cycle represents one group of eggs and embryos. Results can vary between cycles, and factors such as maternal age, the number of embryos tested and individual biology can have a major influence on the outcome.

Depending on your situation, another egg retrieval may be worth considering. In some cases, a mosaic embryo may also be discussed with your fertility specialist and genetic counselor.

Let’s look at what these results actually mean.

Can an IVF Cycle Produce No Euploid Embryos?

Yes.

PGT-A, or Preimplantation Genetic Testing for Aneuploidy, examines cells biopsied from an embryo to assess whether they contain the expected number of chromosomes.

An embryo reported as euploid has the expected chromosome number.

An embryo reported as aneuploid has a chromosome abnormality detected by the test.

It is possible for every embryo tested during one IVF cycle to be reported as aneuploid.

This can be particularly upsetting when several embryos successfully reached the blastocyst stage and appeared healthy under the microscope.

However, embryo appearance and chromosome results are two different things.

A beautiful-looking blastocyst can still be chromosomally abnormal, while morphology alone cannot reliably tell embryologists whether an embryo is euploid.

The chances of having no euploid embryos are influenced by several factors, especially:

  • Maternal age
  • Number of embryos available for testing
  • Egg quality
  • Individual reproductive history
  • Biological variation between cycles

Having no euploid embryos in one cycle therefore does not automatically mean the same result will occur in every future cycle.

Does Age Affect PGT-A Results?

Yes. Maternal age is one of the strongest factors affecting the likelihood of embryo aneuploidy.

Women are born with their lifetime supply of eggs. As reproductive age increases, errors during chromosome separation become more common.

As a result, the proportion of embryos with chromosome abnormalities generally increases with maternal age.

This helps explain why a woman in her early 30s may have a different proportion of euploid embryos than a woman in her early or mid-40s, even if both produce a similar number of blastocysts.

But age provides probabilities—not guarantees.

Two women of exactly the same age can receive very different PGT-A results.

The number of embryos tested also matters.

If only one or two embryos are available, it is entirely possible for neither to be euploid simply because the sample is so small.

Should You Do Another Egg Retrieval?

For many patients, another egg retrieval may be worth discussing.

One IVF cycle does not necessarily predict the outcome of the next cycle.

A second retrieval provides another group of eggs and therefore another opportunity to create embryos.

Whether another cycle makes sense depends on factors such as:

  • Your age
  • AMH and ovarian reserve
  • Number of eggs retrieved previously
  • Number of mature eggs
  • Fertilization rate
  • Number of blastocysts produced
  • Previous PGT-A results
  • Your overall fertility history

Your doctor should review the entire previous cycle rather than looking only at the final PGT-A report.

For example, if many eggs were retrieved but very few reached blastocyst, that tells the fertility team something different from a cycle in which several strong blastocysts were created but all tested aneuploid.

These details can help determine whether changes to the treatment strategy should be considered.

Can a Mosaic Embryo Be Transferred?

Sometimes.

PGT-A results aren’t always simply “normal” or “abnormal.”

Some embryos may be reported as mosaic.

A mosaic result means the biopsy sample contained a mixture of cells with apparently normal and abnormal chromosome findings.

Certain mosaic embryos have resulted in healthy pregnancies and births. However, their implantation potential and reproductive risks can differ depending on the specific mosaic finding.

A mosaic embryo should therefore not automatically be treated the same way as a fully euploid embryo.

If no euploid embryos are available, your fertility specialist may discuss whether a particular mosaic embryo could potentially be considered for transfer.

This decision should involve careful review of:

  • The specific chromosome involved
  • The type and level of mosaicism reported
  • The laboratory report
  • Other embryos available
  • Your medical and fertility history

Genetic counseling is particularly important before considering mosaic embryo transfer.

If pregnancy occurs following transfer of a mosaic embryo, prenatal diagnostic testing may also be discussed.

Does an Abnormal PGT-A Result Mean the Embryo Could Never Become a Healthy Baby?

This is where the conversation becomes more complicated.

PGT-A is a screening test, not a perfect diagnostic test of every cell within an embryo.

Only a small sample of cells from the embryo’s trophectoderm—the part that contributes largely to the placenta—is biopsied.

The test provides valuable information about the chromosome status of those sampled cells, but it does not examine every cell in the embryo.

For this reason, PGT-A results should always be interpreted alongside the laboratory report, clinical history and professional genetic counseling.

Patients should not make decisions about embryos based solely on information found online.

What If Repeated IVF Cycles Produce No Euploid Embryos?

If several cycles repeatedly produce no euploid embryos, your fertility specialist may recommend reviewing the overall treatment strategy.

Depending on age, ovarian reserve and previous results, possibilities may include:

  • Another IVF cycle with your own eggs
  • Changes to ovarian stimulation
  • Further investigation where clinically appropriate
  • A tandem cycle
  • Egg donation

A tandem cycle may be particularly relevant for patients who still want an opportunity to use their own eggs but are concerned about repeatedly producing abnormal embryos.

This approach can involve using the patient’s own eggs alongside donor eggs within the broader treatment cycle, providing another potential pathway if embryos created from the patient’s eggs are unsuccessful.

For some patients—particularly where maternal age and repeated abnormal embryo results are major concerns—egg donation may provide a substantially different probability of obtaining chromosomally healthy embryos because chromosome risk is closely associated with the age of the egg.

But this is a highly personal decision.

There is no point at which every patient should automatically move to donor eggs.

Does Having No Normal Embryos Mean IVF Has Failed?

It can certainly feel that way, but clinically, the cycle has also provided valuable information.

Your fertility team now knows more about:

  • How your ovaries responded to stimulation
  • How many eggs matured
  • How fertilization progressed
  • How embryos developed
  • How many reached blastocyst
  • What the PGT-A results showed

That information can help shape the next treatment decision.

Sometimes another retrieval produces a different result.

Sometimes the previous cycle highlights an area that should be investigated further.

And sometimes the results help patients and their doctors decide that a different pathway—such as tandem treatment or egg donation—may offer a better chance of success.

Final Thoughts

Receiving a PGT-A report showing no euploid embryos can be one of the most difficult moments in IVF.

But one result does not necessarily define your entire fertility journey.

Maternal age, the number of embryos tested, egg quality and natural biological variation can all influence PGT-A results. Another egg retrieval may produce a different group of embryos and potentially a different outcome.

And if a mosaic embryo is available, it may deserve a more detailed conversation rather than being automatically dismissed, depending on the specific result.

The most important next step is to sit down with your fertility specialist and carefully review what happened throughout the entire IVF cycle—not only the final PGT-A result.

Sometimes the next decision is another retrieval. Sometimes it’s further evaluation. And sometimes it’s considering a different route altogether.

The goal isn’t simply to produce as many embryos as possible.

It’s to find the safest and most appropriate path toward a healthy pregnancy.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com
General

What Is a Chemical Pregnancy After IVF? Causes, Implantation and Trying Again

Seeing a positive pregnancy test after IVF can feel like the moment you’ve been waiting for. After medications, egg retrieval, embryo development and finally embryo transfer, a positive beta-hCG result can bring enormous relief.

That’s why being told a few days later that the pregnancy is no longer progressing can be particularly difficult.

This is known as a chemical pregnancy.

A chemical pregnancy is a very early pregnancy loss that happens before the pregnancy can usually be confirmed on ultrasound. Importantly, it means that implantation did begin—the embryo produced enough hCG for a pregnancy test to become positive—but development stopped very early.

So why does this happen, and what does it mean for your next IVF attempt?

What Is a Chemical Pregnancy After IVF?

A chemical pregnancy occurs when an embryo implants sufficiently for the body to begin producing human chorionic gonadotropin (hCG), but the pregnancy stops developing at a very early stage.

After IVF, clinics usually perform a blood test—known as a beta-hCG test—following embryo transfer.

If hCG is detected, the test is considered positive.

Your fertility clinic may then repeat the blood test to see whether the hCG level is rising appropriately.

With a chemical pregnancy, hCG may initially rise but then:

  • Increase more slowly than expected
  • Plateau
  • Begin to fall

Because the pregnancy ends so early, an ultrasound usually does not yet show a gestational sac.

What Causes a Chemical Pregnancy?

There isn’t always a clear answer.

One of the most common reasons for very early pregnancy loss is believed to be chromosomal abnormalities in the embryo.

An embryo may fertilize normally, develop into a blastocyst, look good under the microscope and even begin implantation while still having a chromosomal problem that prevents continued development.

Other factors may sometimes contribute, including:

  • Embryo-related factors
  • Maternal age
  • Uterine abnormalities
  • Hormonal factors
  • Certain underlying medical conditions

However, experiencing one chemical pregnancy does not automatically mean there is an underlying fertility problem beyond the reason IVF was needed in the first place.

Very early pregnancy loss can also occur during natural conception.

Does a Chemical Pregnancy Mean the Embryo Implanted?

Yes.

This is an important point.

For hCG to become detectable following embryo transfer, implantation must have started.

The embryo reached the uterus, interacted with the endometrium and began the implantation process.

Unfortunately, development then stopped before the pregnancy progressed far enough to be seen on ultrasound.

Although a chemical pregnancy is still a pregnancy loss, the fact that implantation occurred can provide your fertility specialist with useful information about the cycle.

It demonstrates that implantation was possible.

Does a Chemical Pregnancy Mean Something Is Wrong With Your Embryos?

Not necessarily.

A single chemical pregnancy does not mean that all of your embryos are abnormal or that future embryo transfers will fail.

Embryos created during the same IVF cycle can be very different from one another.

One embryo may be chromosomally abnormal while another from the same retrieval may have the potential to develop into a healthy pregnancy.

This is particularly important to understand when frozen embryos remain from the original IVF cycle.

Having one chemical pregnancy does not automatically mean those remaining embryos will have the same outcome.

Can a Good-Quality Embryo Cause a Chemical Pregnancy?

Yes.

Embryo grading and chromosome status are not the same thing.

When an embryologist describes an embryo as “good quality,” they are generally assessing its development and appearance under the microscope.

An embryo can look excellent but still carry a chromosomal abnormality.

This is one reason why embryo appearance alone cannot guarantee implantation, pregnancy or a healthy birth.

Does Age Affect the Risk?

Age can be an important factor because the likelihood of chromosomal abnormalities in eggs generally increases as maternal age rises.

As a result, the chance of creating chromosomally abnormal embryos also increases.

However, chemical pregnancies can occur at any reproductive age.

Age changes the probability; it does not determine the outcome of every individual embryo.

When Can You Try IVF Again After a Chemical Pregnancy?

Many patients immediately ask:

“How long do I have to wait before trying again?”

There is no universal waiting period.

Because a chemical pregnancy occurs very early, physical recovery can be relatively quick. However, your fertility clinic will usually want to confirm that hCG has returned to a non-pregnant level and that you are medically ready before beginning another treatment cycle or embryo transfer.

Some patients may be able to proceed relatively soon, potentially with a subsequent menstrual cycle.

Others may be advised to wait longer depending on:

  • hCG levels
  • Menstrual recovery
  • The IVF protocol being planned
  • Uterine health
  • Whether additional investigation is needed
  • Physical and emotional readiness

Your fertility specialist should determine the appropriate timing for your individual situation.

What Happens to Your IVF Medications?

Do not stop progesterone, estrogen or other prescribed IVF medications simply because of spotting or because a home pregnancy test changes.

Your fertility clinic will normally use blood tests to determine what is happening.

If a chemical pregnancy is confirmed, your doctor will tell you when and how to discontinue medications.

Always follow the instructions of your fertility team.

Should You Have Tests After a Chemical Pregnancy?

After one isolated chemical pregnancy, extensive testing is not necessarily required.

Very early pregnancy losses are unfortunately common.

The situation may be different when there are repeated chemical pregnancies, recurrent miscarriages or repeated implantation failures.

Your fertility specialist may then review factors such as:

  • Embryo development
  • Uterine anatomy
  • Endometrial health
  • Hormonal factors
  • Parental medical history
  • Sperm factors
  • Whether genetic testing is appropriate

Testing should be targeted to the individual patient rather than automatically ordering every available fertility test.

Can You Have a Successful Pregnancy After a Chemical Pregnancy?

Absolutely.

A chemical pregnancy does not mean that IVF will never work.

Many patients who experience an early loss later achieve an ongoing pregnancy, whether through another frozen embryo transfer or a subsequent IVF cycle.

The next step depends on why IVF was originally required, the patient’s age, embryo availability and what was learned from the previous cycle.

What If Chemical Pregnancies Keep Happening?

One chemical pregnancy and repeated chemical pregnancies are different situations.

If early losses happen repeatedly, your fertility specialist may recommend a more detailed investigation.

The goal is to determine whether there is a recurring embryo-related, uterine, hormonal, genetic or other factor that deserves attention before another transfer.

For some patients, the IVF strategy may then be adjusted based on the findings.

Final Thoughts

A chemical pregnancy after IVF means that implantation began, but the pregnancy stopped developing at a very early stage.

It does not mean you did something wrong.

It also doesn’t automatically mean your remaining embryos are unhealthy or that another IVF attempt will fail.

Chromosomal abnormalities are an important cause of very early pregnancy loss, but sometimes there is simply no definitive explanation for why one particular embryo stopped developing.

After a chemical pregnancy, your fertility specialist can review your embryo development, beta-hCG results and treatment history to decide whether anything should be changed before trying again.

And perhaps the most important thing to remember is this:

A chemical pregnancy is not the end of your IVF journey.

For many patients, the next transfer or treatment cycle can have a completely different outcome.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com

General

Understanding Embryo Arrest During IVF:Why Did My Embryo Stop Growing?

Embryo arrest during IVF treatment can cause a lot of confusion, and panic amongst patients. One of the hardest updates to receive during IVF is hearing that an embryo has stopped developing.

Egg retrieval may have gone well. Fertilization may have occurred normally. Then, over the following days, the embryology laboratory reports that one or more embryos are no longer progressing.

Naturally, patients want to know why.

Embryo development is an incredibly complex biological process. Not every fertilized egg will become a blastocyst, and an embryo stopping during development does not necessarily mean something went wrong in the laboratory.

Egg quality, sperm quality, chromosomal abnormalities and the embryo’s own developmental potential can all play a role.

Why Do Embryos Stop Developing After Fertilization?

Fertilization is only the beginning.

Once an egg has been fertilized, the resulting embryo must repeatedly divide its cells while activating and regulating thousands of biological processes.

Some embryos simply do not have the biological potential to continue developing.

One important reason is chromosomal abnormality. An embryo may contain too many or too few chromosomes, which can interfere with normal development.

Other possible factors include:

  • Egg quality
  • Sperm quality
  • DNA damage
  • Problems during cell division
  • Maternal age
  • Laboratory and culture conditions

In many cases, there isn’t one simple explanation.

An embryo can look promising during its first few days and still stop developing later.

Why Do Embryos Stop Growing Before Day 5?

During IVF, embryos are commonly cultured in the laboratory until approximately Day 5 or Day 6, when successfully developing embryos may reach the blastocyst stage.

But not every fertilized egg will make it that far.

An embryo that looks good on Day 3 may slow down or stop before reaching blastocyst.

This period involves major developmental changes. The embryo must continue dividing, organize its cells and activate its own genome.

Embryologists monitor this progression closely, but they cannot force an embryo to continue developing.

This is also why the number of embryos usually decreases at each stage of IVF.

For example, the number of eggs retrieved is not expected to equal the number of blastocysts ultimately available for transfer or freezing.

Some natural attrition during embryo development is expected.

Does Poor Egg Quality Cause Embryo Arrest?

Yes, egg quality can be an important factor.

The egg contributes much of the cellular machinery needed during the earliest stages of embryo development.

As women get older, the likelihood of chromosomal abnormalities in their eggs generally increases. This is one of the main reasons IVF success rates tend to decline with maternal age.

Poor egg quality may contribute to:

  • Failed fertilization
  • Abnormal cell division
  • Slow embryo development
  • Embryo arrest
  • Failure to reach blastocyst
  • Chromosomally abnormal embryos

However, low ovarian reserve and poor egg quality are not exactly the same thing.

A woman with low AMH may produce fewer eggs, but those eggs are not automatically poor quality. Age remains one of the strongest indicators of the likelihood of chromosomal abnormalities.

Can Sperm Quality Cause Embryos to Stop Developing?

Yes.

IVF is not only about the egg.

The sperm contributes half of the embryo’s genetic material, and significant problems with sperm quality can potentially affect fertilization and subsequent embryo development.

One area fertility specialists may investigate is sperm DNA fragmentation.

A standard semen analysis looks at factors such as:

  • Sperm concentration
  • Movement (motility)
  • Morphology
  • Semen volume

But sperm that appears relatively normal on a standard semen analysis may still have increased DNA fragmentation.

Higher sperm DNA fragmentation has been associated with poorer reproductive outcomes in some circumstances, although its exact clinical importance varies between patients.

If repeated IVF cycles show unexpectedly poor embryo development, your fertility specialist may therefore consider both female and male factors rather than assuming the eggs are responsible.

If My Embryos Stop Growing, Does It Mean IVF Won’t Work?

No.

One unsuccessful cycle does not necessarily predict what will happen during the next one.

IVF also provides doctors and embryologists with valuable information about how your eggs, sperm and embryos behave in the laboratory.

After significant embryo arrest, your fertility team may review:

  • Ovarian stimulation response
  • Number of mature eggs
  • Fertilization rate
  • Sperm parameters
  • Embryo development from Day 1 onward
  • Maternal and paternal age
  • Previous IVF history

Depending on the findings, the treatment strategy may be adjusted before another attempt.

What Can Be Done After Embryo Arrest?

There is no single treatment for embryo arrest because the underlying reason can differ from patient to patient.

Your fertility specialist may recommend further evaluation of egg and sperm factors, modifications to the IVF protocol or additional testing where clinically appropriate.

For patients with repeated poor embryo development related to significant concerns about egg quality, options such as egg donation or a tandem cycle may eventually be discussed.

A tandem cycle allows a patient’s own eggs and donor eggs to be used within the treatment strategy, providing another option for patients who still want an opportunity to attempt IVF with their own eggs while also having donor eggs available.

This isn’t necessary for everyone, and the decision should be based on the patient’s age, ovarian reserve, previous IVF results and individual circumstances.

Does One Arrested Embryo Mean All My Embryos Are Abnormal?

No.

Embryos from the same IVF cycle can behave very differently.

One embryo may stop developing on Day 3 while another reaches a high-quality blastocyst on Day 5 or Day 6.

This is why embryologists monitor each embryo individually.

Ultimately, IVF isn’t about getting every fertilized egg to become a blastocyst. The goal is to identify the embryo or embryos with the strongest potential for a healthy pregnancy.

Final Thoughts

Watching embryo numbers decrease between fertilization and Day 5 can be one of the most stressful parts of IVF.

But some degree of embryo attrition is a normal part of human reproduction.

When embryos repeatedly stop developing, the important question isn’t simply “Why did my IVF fail?”

It’s:

“What did this cycle teach us?”

Egg quality, sperm quality, chromosomal abnormalities and embryo biology can all contribute to developmental arrest.

By carefully reviewing what happened at each stage, an experienced fertility team can determine whether additional testing, a different IVF protocol or another treatment approach should be considered.

Sometimes the information gained from one difficult cycle becomes exactly what is needed to plan the next one.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com
General

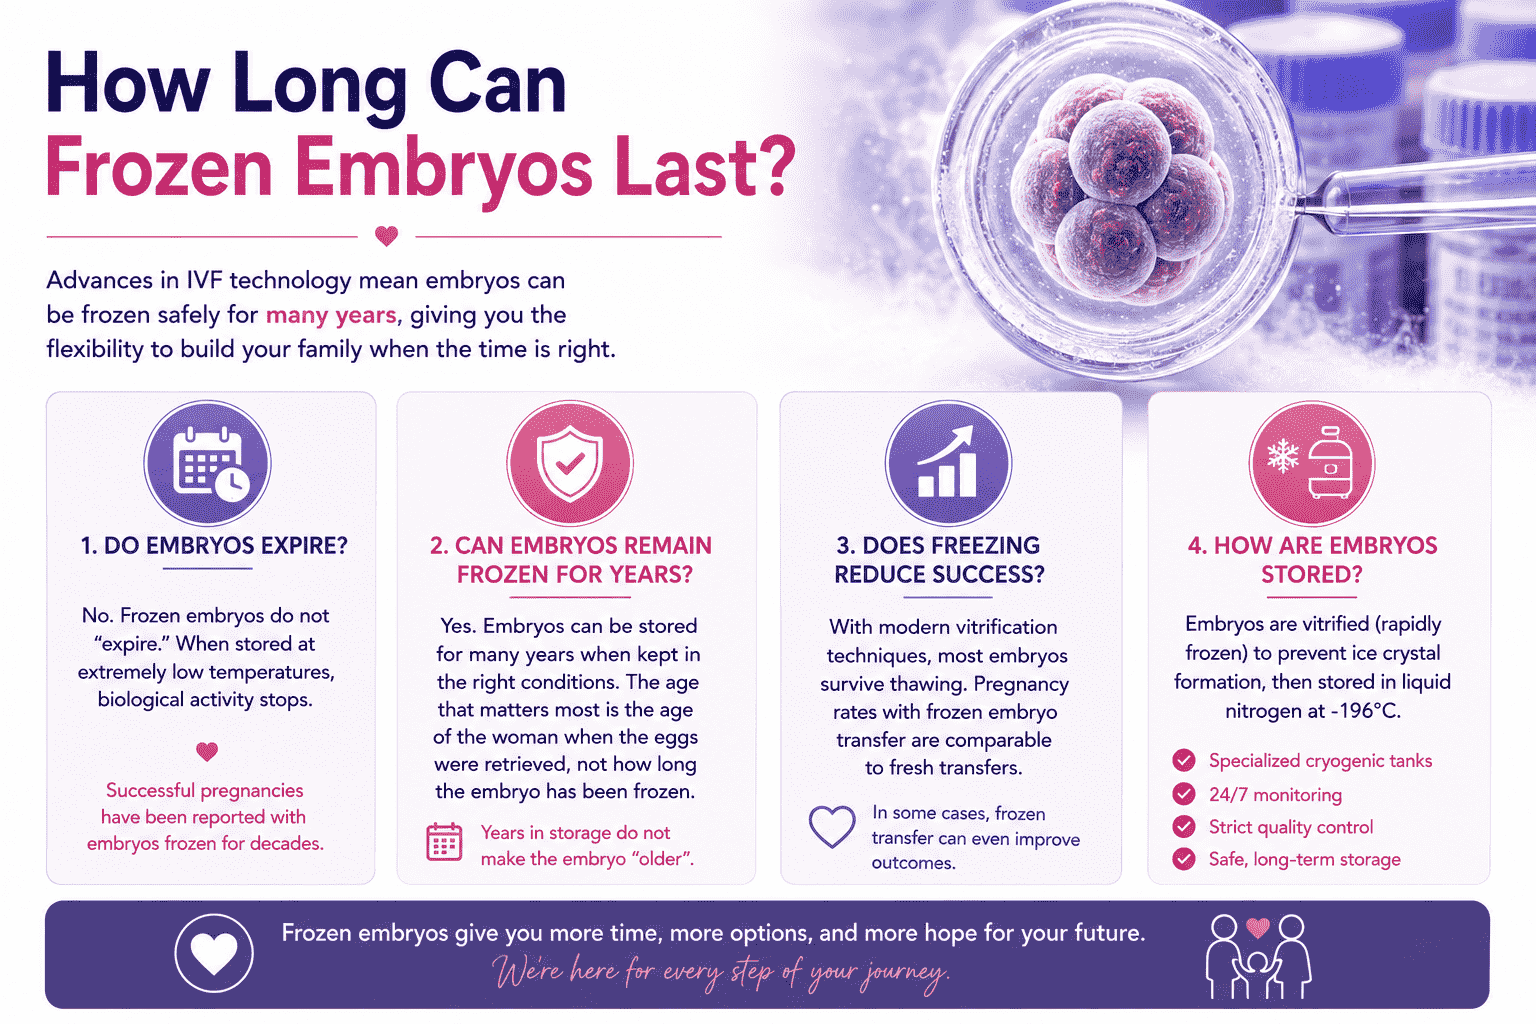
How Long Can Frozen Embryos Last? What IVF Patients Should Know

Embryo freezing has become an important part of modern IVF. It allows patients to preserve embryos for a future pregnancy, delay embryo transfer when necessary, or potentially try for another child years after their original IVF treatment.

But one question comes up again and again:

How long can frozen embryos actually last?

The answer may be surprising. When embryos are properly frozen and continuously stored under the correct laboratory conditions, there is no established biological “expiration date” after just a few years. Healthy births have been reported using embryos that were frozen for decades.

The bigger considerations are usually storage conditions, clinic policies, local regulations, and how long the patient wishes to continue storage.

Do Embryos Expire?

Frozen embryos do not “expire” in the same way that food or medication does.

Modern IVF laboratories commonly use a rapid-freezing technique called vitrification. This brings embryos to extremely low temperatures and essentially pauses biological activity.

While the embryo remains correctly cryopreserved, it does not continue developing or aging in the way it would inside the body.

This means that an embryo stored for several years isn’t biologically several years “older.”

The age that matters most for embryo-related outcomes is generally the age of the woman or egg donor when the eggs were retrieved, rather than how many years the resulting embryo has spent frozen.

There can, however, be legal or administrative limits on embryo storage depending on the country and clinic.

Can Embryos Remain Frozen for Years?

Yes.

Embryos can potentially remain frozen for many years when maintained under appropriate conditions.

There have even been successful pregnancies and healthy births from embryos stored for decades.

This is particularly important for patients who:

  • Want another child later
  • Need to postpone pregnancy
  • Have completed IVF but aren’t ready for transfer
  • Want to preserve embryos before certain medical treatments
  • Have additional embryos remaining after a successful IVF cycle

For some families, frozen embryos can provide an opportunity to return years later for another pregnancy without repeating the entire ovarian stimulation and egg retrieval process.

How Are Embryos Stored?

After fertilization, embryos are carefully monitored as they develop in the embryology laboratory.

Embryos suitable for freezing are commonly preserved using vitrification.

Instead of slowly freezing the embryo, vitrification cools it extremely rapidly. This helps minimize the formation of damaging ice crystals within the cells.

Once vitrified, embryos are stored in specialized cryogenic tanks containing liquid nitrogen at temperatures of approximately -196°C (-321°F).

The laboratory plays an extremely important role here.

Cryogenic storage systems require careful identification procedures, monitoring, quality control, and protocols designed to keep embryos safely stored over long periods.

When a patient is ready for treatment, the selected embryo is carefully warmed and assessed by the embryology team before transfer.

Does Freezing Reduce IVF Success?

This is one of the biggest concerns patients have about embryo freezing.

With modern vitrification techniques, most suitable embryos survive the freezing and warming process, although no laboratory procedure can guarantee that every embryo will survive.

Importantly, frozen embryo transfer is now a routine part of IVF treatment worldwide.

For many patients, pregnancy rates with frozen embryo transfers can be comparable to fresh transfers. In some circumstances, a fertility specialist may actually prefer a frozen transfer.

This can allow the ovaries and hormone levels to settle after stimulation while the uterus is prepared separately for embryo transfer.

Whether fresh or frozen transfer is preferable depends on the individual patient and treatment cycle.

Does an Embryo Lose Quality While It Is Frozen?

Properly cryopreserved embryos are maintained in a state where biological activity is essentially suspended.

They aren’t continuously growing or aging while in storage.

Therefore, simply keeping an embryo frozen for several years does not mean that it gradually becomes “older” in the same way a person’s eggs naturally age inside the ovaries.

What matters much more is the quality of the embryo when it was frozen and the conditions under which it was frozen, stored, and eventually warmed.

Does My Age Matter When I Use a Frozen Embryo?

Yes—but there is an important distinction.

Imagine a woman creates and freezes embryos at age 30 and returns to use one at age 38.

The embryo was created from eggs retrieved when she was 30. Therefore, many embryo-related risks are more closely associated with her age at egg retrieval.

However, her health and age at the time of pregnancy still matter.

Pregnancy itself can carry additional risks as maternal age increases, so a medical evaluation may be recommended before embryo transfer.

Why Do IVF Clinics Freeze Embryos?

There are many reasons embryos may be frozen rather than transferred immediately.

These include:

  • Additional good-quality embryos remaining after IVF
  • Planning a frozen embryo transfer
  • Genetic testing such as PGT
  • Concerns about ovarian hyperstimulation syndrome (OHSS)
  • The uterine lining not being ready for transfer
  • Fertility preservation
  • Planning future pregnancies

Embryo freezing gives fertility specialists and patients greater flexibility when planning treatment.

What Happens When You’re Ready to Use a Frozen Embryo?

When you’re ready for a frozen embryo transfer, your fertility team will first prepare and evaluate the uterus.

The uterine lining may be prepared through a natural cycle or with medication, depending on the patient’s circumstances.

The embryo is then warmed in the laboratory.

Embryologists check that it has survived the warming process and assess its condition before transfer.

The embryo is then placed directly into the uterus using a thin catheter.

From that point onward, implantation occurs in essentially the same way as with an embryo transferred during a fresh IVF cycle.

Can Frozen Embryos Be Used for Another Baby Years Later?

Yes.

This is one of the major advantages of embryo freezing.

A couple may complete IVF, have their first child, and keep additional embryos frozen.

Several years later, they may return to use one of those embryos in an attempt to have another child.

Because the embryos were created during the original IVF cycle, the eggs used to create them remain associated with the woman’s age at the time they were retrieved.

This can make embryo freezing particularly valuable for family planning.

Final Thoughts

So, how long can frozen embryos last?

Frozen embryos may last for many years—and even decades—when they are properly vitrified and continuously maintained under appropriate cryogenic storage conditions.

Embryos do not simply become too old because they have spent several years frozen. Modern vitrification essentially pauses their biological development until they are warmed for treatment.

What matters most is the quality of the embryo when it was created, the expertise of the embryology laboratory, proper long-term storage, and careful warming before transfer.

If you have frozen embryos or are considering embryo freezing, speak with your fertility clinic about its storage procedures, fees, consent requirements, and any legal storage limits that apply where your embryos are kept.

Embryo freezing isn’t simply about preserving an embryo today. For many families, it preserves an opportunity they may choose to return to years into the future.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com
General

Why Are IVF Success Rates Different Between Clinics? What Patients Should Really Look For

IVF success rates are connected to many factors such as, genetics, egg quality, sperm quality, and of course the right clinic.

Today we are going to cover why IVF success rates greatly depend on choosing the right clinic.

Choosing an IVF clinic can feel overwhelming. One clinic advertises an 80% success rate, another claims 90%, while others avoid publishing their numbers altogether.

It’s natural to wonder:

“Why are IVF success rates so different between clinics?”

The truth is that success rates are influenced by many factors. Experience, laboratory quality, patient selection, embryo development, and individualized treatment all play an important role.

While success rates are useful, they should never be the only reason for choosing a fertility clinic.

Let’s explore why these numbers vary and what you should really be looking for.

Why Are IVF Success Rates Different Between Clinics?

There is no single factor that determines IVF success.

Every clinic treats a different patient population. Some clinics accept more complex cases, while others may mainly treat younger patients with fewer fertility challenges.

Success rates are also influenced by:

  • The age of the patient
  • Egg quality
  • Sperm quality
  • Embryology laboratory standards
  • The experience of the fertility team
  • The technologies used during IVF
  • Individualized treatment planning

Because every clinic is different, comparing success rates alone does not always provide the full picture.

What Is a Good Success Rate for IVF?

This is one of the most searched fertility questions online.

There is no universal percentage that applies to every patient.

Success rates naturally vary depending on factors such as:

  • Maternal age
  • Ovarian reserve
  • Embryo quality
  • Whether donor eggs are used
  • Previous fertility history

Rather than focusing on one advertised percentage, ask your clinic about success rates for patients with a similar age and fertility diagnosis to your own.

That information is usually far more meaningful.

Why Do Some IVF Clinics Have Better Results?

Behind every successful IVF cycle is an experienced multidisciplinary team.

A successful clinic relies on:

  • Skilled fertility specialists
  • Experienced embryologists
  • High laboratory standards
  • Advanced equipment
  • Personalized treatment protocols
  • Continuous quality control

One of the most important—but often overlooked—factors is the embryology laboratory.

Embryos spend several days developing inside the laboratory before transfer. Maintaining the right environment throughout this process is essential for healthy embryo development.

Does the Embryology Laboratory Matter?

Absolutely.

Many fertility specialists consider the embryology laboratory to be the heart of an IVF clinic.

Temperature control, air quality, laboratory protocols, and the expertise of embryologists all contribute to embryo development.

Even small differences in laboratory quality can influence treatment outcomes.

This is why experienced embryology teams play such an important role in modern IVF.

Why Patients Choose Our IVF Clinics

At Crown IVF, American IVF, and Clavis IVF, patients benefit from decades of combined experience under the medical leadership of Dr. Halil İbrahim Tekin (Dr. HIT), one of the most experienced fertility specialists in Cyprus.

Throughout his career, Dr. HIT has helped thousands of couples from around the world begin their families.

His commitment to quality extends beyond patient consultations.

The embryology laboratories and quality standards across our partner clinics are guided by Dr. HIT and his experienced embryology and laboratory team, ensuring consistent attention to every stage of embryo development.

By combining experienced physicians, highly trained embryologists, and modern IVF technologies, our clinics strive to provide patients with safe, personalized fertility care.

Why Patients Travel to Cyprus for IVF

North Cyprus has become one of the most popular destinations for fertility treatment.

Patients travel from:

  • Europe
  • The United Kingdom
  • The Middle East
  • Africa
  • North America

Many choose Cyprus because of:

  • Affordable treatment costs
  • Short waiting times
  • Advanced IVF technology
  • Experienced fertility specialists
  • Personalized care
  • Convenient travel

At Crown IVF, American IVF, and Clavis IVF, we also offer treatment packages and guarantee programs designed to give international patients greater confidence and peace of mind throughout their fertility journey.

How Do I Choose the Right IVF Clinic?

When comparing clinics, ask questions such as:

  • Who will oversee my treatment?
  • How experienced is the embryology laboratory?
  • Is my treatment plan personalized?
  • What technology does the clinic use?
  • What support is available for international patients?
  • What do previous patients say about their experience?

The right clinic is not always the one with the biggest advertised number.

It is the one that offers the expertise, transparency, and individualized care that best fits your unique situation.

Final Thoughts

IVF success rates vary for many reasons, and no single percentage can predict an individual’s chances of pregnancy.

Behind every successful treatment is a combination of medical expertise, experienced embryologists, advanced laboratory standards, and personalized patient care.

At Crown IVF, American IVF, and Clavis IVF, we are proud to combine affordable treatment with decades of experience under the leadership of Dr. Halil İbrahim Tekin (Dr. HIT). By maintaining high laboratory standards and providing individualized fertility care, our goal is to help every patient receive the best possible opportunity to build their family.

Because in fertility treatment, experience, quality, and trust matter just as much as the numbers.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com
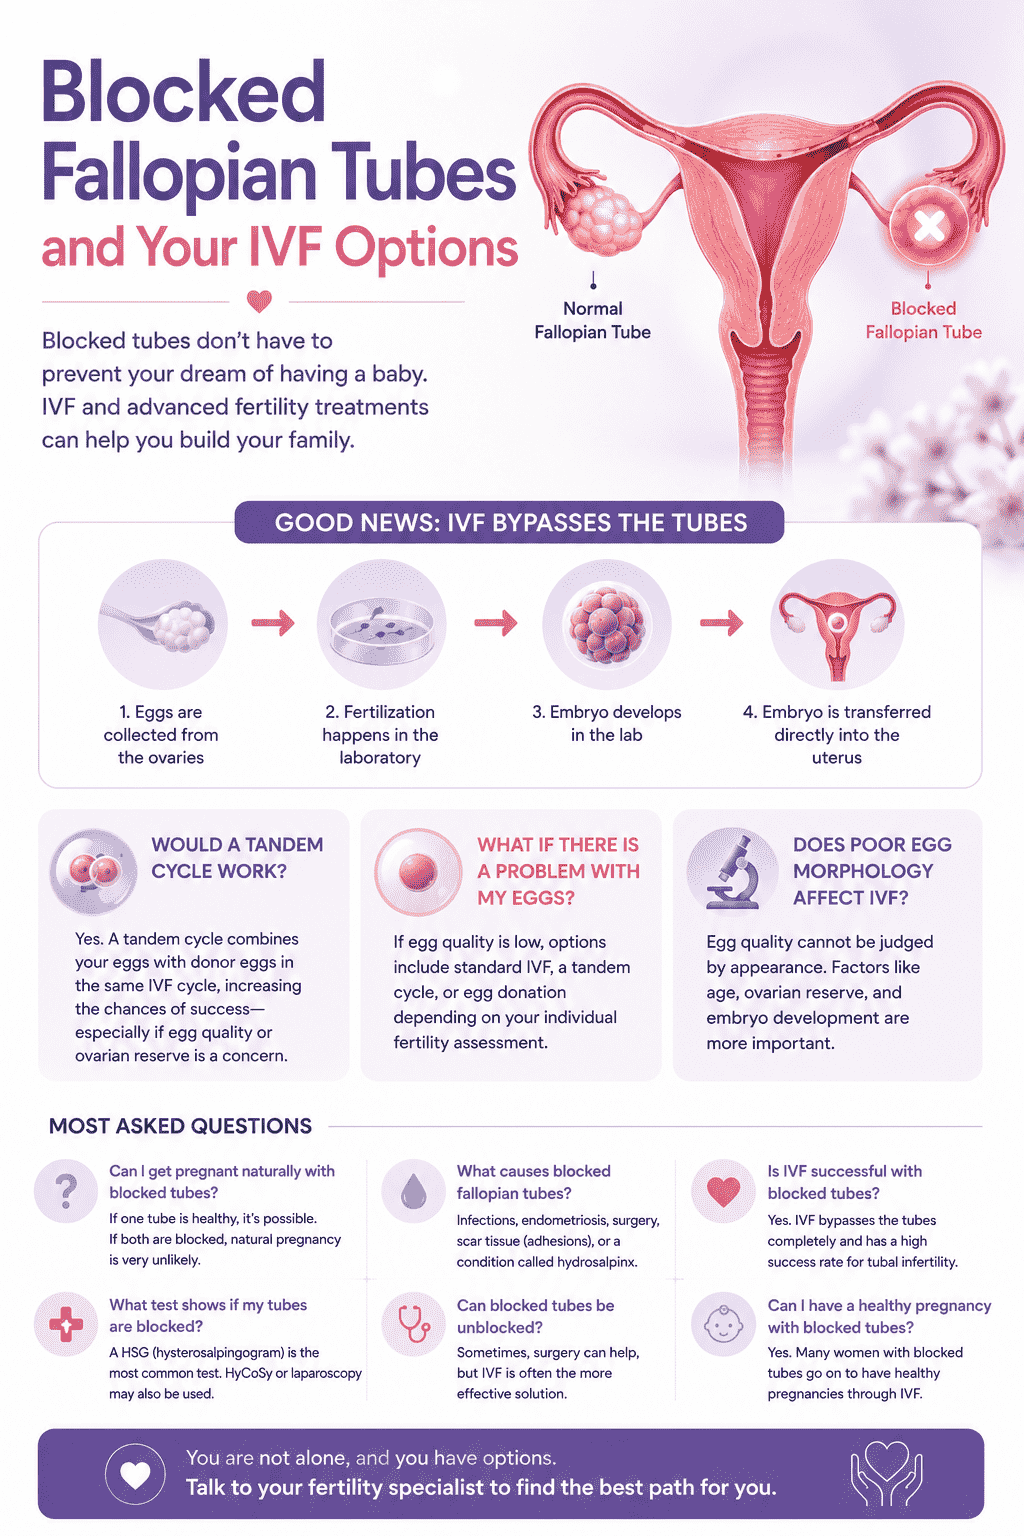
General

Blocked Fallopian Tubes and IVF: Can You Still Get Pregnant?

Being told that one or both of your fallopian tubes are blocked can be overwhelming. For many couples, it’s one of the first explanations they receive after months—or even years—of trying to conceive.

The good news is that blocked fallopian tubes do not necessarily mean you cannot become pregnant.

Modern fertility treatments have made it possible for many women with tubal infertility to build their families. However, treatment depends on more than just the condition of the fallopian tubes. Egg quality, sperm quality, age, and overall reproductive health all play an important role in determining the most suitable approach.

Let’s explore what blocked fallopian tubes mean and the options that may be available.

What Happens If Your Fallopian Tubes Are Blocked?

The fallopian tubes connect the ovaries to the uterus.

During natural conception:

  • The egg is released from the ovary.
  • Fertilization usually occurs inside the fallopian tube.
  • The fertilized embryo then travels into the uterus for implantation.

If one or both tubes are blocked, the egg and sperm may never meet, making natural pregnancy much more difficult.

The blockage may be caused by:

  • Previous pelvic infections
  • Endometriosis
  • Previous abdominal or pelvic surgery
  • Scar tissue (adhesions)
  • Hydrosalpinx (fluid-filled fallopian tube)

Some women have no symptoms at all and only discover the blockage during fertility testing.

Can You Get Pregnant Naturally With Blocked Fallopian Tubes?

It depends.

If only one tube is blocked and the other tube is healthy, natural pregnancy is still possible.

If both tubes are completely blocked, natural conception becomes very unlikely because fertilization cannot take place inside the tubes.

In these situations, IVF is often the recommended treatment because it bypasses the fallopian tubes completely.

Is IVF Successful With Blocked Fallopian Tubes?

Yes.

Blocked fallopian tubes are actually one of the most treatable causes of infertility.

During IVF:

  • Eggs are collected directly from the ovaries.
  • Fertilization takes place in the laboratory.
  • The embryo is transferred directly into the uterus.

Because the fallopian tubes are bypassed, many women with tubal infertility achieve successful pregnancies through IVF.

However, if a woman has a condition called hydrosalpinx, where a tube is filled with fluid, treatment of the affected tube may be recommended before embryo transfer because the fluid can reduce implantation rates.

Would a Tandem Cycle Work If My Fallopian Tubes Are Blocked?

In many cases, yes.

A tandem cycle combines a patient’s own eggs with donor eggs during the same IVF treatment.

This approach may be considered when a patient has:

  • Blocked fallopian tubes
  • Reduced ovarian reserve
  • Poor egg quality
  • Advanced maternal age

Because IVF bypasses the fallopian tubes, the blockage itself does not prevent a tandem cycle.

The decision depends more on ovarian function and the quality of the patient’s own eggs than on the condition of the tubes.

What If There Is a Problem With My Eggs?

Blocked fallopian tubes are only one part of fertility.

If testing also shows:

  • Poor egg quality
  • Low ovarian reserve
  • Repeated abnormal embryos
  • Advanced maternal age

your fertility specialist may discuss additional options.

These may include:

Standard IVF

If there are still healthy eggs available, IVF using your own eggs may remain the best option.

Tandem Cycle

Patients who still produce some eggs but have concerns about egg quality may consider combining their own eggs with donor eggs during the same treatment cycle.

This allows the opportunity for pregnancy using either source of eggs, depending on embryo development.

Egg Donation

If ovarian reserve is extremely low or egg quality has declined significantly, egg donation may offer the highest chance of achieving pregnancy.

The most appropriate option depends on your individual fertility assessment.

Does Poor Egg Morphology Affect IVF?

The word morphology is most commonly used to describe the appearance of sperm, rather than eggs.

Unlike sperm, egg quality cannot be judged by appearance alone.

Doctors evaluate egg quality using several factors, including:

  • Maternal age
  • Ovarian reserve
  • Egg maturity
  • Fertilization rates
  • Embryo development

If embryo development repeatedly shows poor quality despite IVF, your fertility specialist may recommend additional testing or discuss alternative treatment options.

Can Blocked Fallopian Tubes Be Unblocked?

Sometimes.

Treatment depends on where the blockage is located and what caused it.

In selected cases, surgery may reopen a blocked tube.

However, surgery is not appropriate for everyone, and IVF is often the more effective treatment—particularly if both tubes are severely damaged or blocked.

Your fertility specialist will recommend the approach most likely to result in a healthy pregnancy.

What Test Shows If My Fallopian Tubes Are Blocked?

The most common test is a Hysterosalpingogram (HSG).

During this procedure:

  • A special dye is placed inside the uterus.
  • X-rays show whether the dye passes through the fallopian tubes.

Other tests that may be used include:

  • HyCoSy (ultrasound with contrast)
  • Laparoscopy in selected patients

These investigations help determine whether one or both tubes are blocked.

Final Thoughts

Blocked fallopian tubes are a common cause of infertility, but they are also one of the conditions for which IVF has been especially successful.

Because IVF bypasses the tubes entirely, many women with tubal infertility go on to achieve healthy pregnancies.

If blocked tubes are combined with poor ovarian reserve or concerns about egg quality, additional options such as a tandem cycle or egg donation may be discussed to maximize the chances of success.

Every fertility journey is unique.

The most important step is receiving a thorough evaluation from an experienced fertility specialist who can recommend a treatment plan based on your individual diagnosis—not just one test result.

With today’s fertility treatments, blocked fallopian tubes are no longer the obstacle they once were, and for many couples, parenthood remains very much within reach.

For any of your fertility problems, please do not hesitate to contact us. At Fertility Solutions we pride ourselves with the excellent tailored personal care we provide to our patients for their specific needs. A team member will contact you as soon as we get your message, and construct a personal treatment plan for your fertility problems in the country of Cyprus. You can also contact our clinics directly through the links below.

Get in Touch with Our Clinics:

Cyprus Crown IVF Contact: https://en.cypruscrownivf.com/contact

Cyprus American IVF Contact: https://www.cyprusamericanivf.com/contact-us/

Dr. Halil Ibrahim Tekin  (Dr. HIT) Youtube: https://www.youtube.com/@dr.halilibrahimtekin1715

Cyprus American IVF Youtube: https://www.youtube.com/@AmerikanTupBebekMerkezi

Clavis Fertility Centre: https://www.clavisfertilitycenter.com


Notice: ob_end_flush(): Failed to send buffer of zlib output compression (0) in /home/fertilitysol/public_html/wp-includes/functions.php on line 5581